microbiome

Gene-level pangenome analysis and the colorectal-cancer microbiome

Today I want to tell you about a recently published paper that I was a part of because it’s one that I’m really excited about, both for the findings and the methods. I’m going to start with the findings and then go back and explain how we got there.

The paper: Pangenome analysis reveals both niche-specific “specialists” and microbial “side hustlers” in colorectal cancer microbiomes. doi: 10.1080/19490976.2026.2728331

The biological question we were interested in was, “What is different about the bacteria present in the intestine (gut microbiome) of people with colorectal cancer (CRC) compared to people without this disease?” The motivation for this question is that we are looking for clues that will help us improve the state-of-the-art methods for preventing, detecting, and/or treating this disease. Of course, there are lots of unhelpful reasons why the gut microbiome could be different, such as the altered physiology of CRC making it easier for certain bacteria to grow, and so we think of these surveys as an initial step that can feed into controlled lab-based experiments. This question has been asked by many groups in lots of different ways over the years, and so what we did in this study was to apply a new data analysis approach to public datasets published by a handful of groups from around the world. Each of these datasets took considerable time, expense, and expertise to collect. We are grateful for the willingness of study participants to support scientific progress by making this contribution to the research community.

Previous work in this field has found that there are particular species of bacteria which tend to be found more commonly or abundantly in the gut microbiome of people with CRC, and other species which are found less commonly or abundantly. Other groups have identified differences in the prevalence of metabolic pathways shared across diverse organisms, and still others have measured differences down to the level of specific molecules. If I were to distill my understanding of the field into a vastly oversimplified soundbite, I would say that each study does find some difference in the CRC microbiome, but it is very hard to figure out from these observational studies which of these bacterial differences play a causal role and would therefore be the highest priority for developing preventions and therapeutics. For that, the observations from survey data must be transformed into falsifiable hypotheses which can be tested directly.

There has been groundbreaking work in the last few years that has identified specific bacteria and mechanisms which can reproducibly cause CRC in controlled experimental settings (animal models). While I cannot do justice to that field in this space, I will call out the work of Dr. Susan Bullman (MD Anderson Cancer Center) who has pioneered discoveries on a specific bacterium, Fusobacterium animalis, and its role in CRC. My thinking in this field was influenced greatly by a project in the Bulllman Lab that I was able to contribute some analysis tools to. In this work, Dr. Bullman’s group found that there was a previously-unrecognized subspecies of F. animalis which was far more carcinogenic than the other closely-related bacteria from the same species. In other words, they found that there was a biologically meaningful grouping of bacteria that did not correspond to any previously-recognized species or subspecies, and that group played a distinct role in causing human cancer.

In our recent paper, we expanded on our previous work and went looking for more cases like this, namely previously-unrecognized groups of bacteria hidden within species that had previously been identified as being associated in some way with CRC. We did end up finding some new examples that fit this pattern, with the top example being a lineage of Fusobacterium defined by the presence of a particular grouping of genes (an ‘operon’) encoding genes related to nutrient acquisition in low-glucose environments. We observed that this group of genes was present in a higher proportion of Fusobacterium genomes in the gut microbiome of participants with CRC, and lower proportions from healthy controls. This pattern was consistent across three independent studies performed in different parts of the world. While we have no data suggesting that this has identified any new cause of CRC, it would be possible to test that hypothesis by comparing specific examples of this bacterium with and without that group of genes.

Instead of listing lots of specific bacteria, I’d like to draw your attention to the way in which we ended up identifying them. The key identifying feature we used was whether those bacterial genomes encoded a particular set of genes. Bacteria tend to pass around groups of genes (horizontal gene transfer), and so it’s nice to track those genetic elements explicitly. More importantly, all of the results that we report from this survey are tied to groups of genes which are encoded by particular strains of a known species. The causal hypothesis can be tested in a very straightforward way – compare strains with those genes against strains lacking them.  The actual experimental testing isn’t straightforward at all, but the comparison (bacteria plus or minus certain genes) is the bedrock of molecular biology.

Lastly, let’s talk about how we analyzed the data. You’ll notice that there were multiple bacterial species and multiple microbiome surveys. The compute intensive steps (organizing the gene content for each species, aligning a single microbiome survey against a single species’ genes) are all completely isolated and modular. This is really nice because it means you can add a species or a survey to the analysis without having to redo any of the previous steps. All of the outputs only get pulled together in the final steps. The whole thing is performed using the gig-map suite of Nextflow workflows that I’ve been working on for a few years. Each step is configured to run within the Cirro Data Platform (which has now spun out of Fred Hutch, and is where I work), which makes it easy for non-computational scientists to kick off complex workflows. My hope is that others who want to use the same approach for their own projects will find this relatively easy to use.

If you’ve made it this far, I’ll leave you with a philosophical thought. Bacteria are incredibly diverse and constantly exchanging small pieces of their genomes. This gives us a huge opportunity to map associations of human disease down to individual genes and operons. Those genes and operons also happen to be the most experimentally tractable unit of information to work with. Getting that level of resolution in an animal model would require some immensely large number of generations on the scale of the Collaborative Cross, but we get it with bacteria for free. What this approach gives us is an incredibly efficient way of generating hypotheses that can be tested in the lab. If I had the funding and time to run a research lab, I would develop a meaningful model of an important disease (like CRC), fill up a few freezers with isolates of interesting bacteria, and then sequence all of their genomes. Every new microbiome survey that’s published would then just add more information to prioritize which genes to investigate, with the luxury of a complete inventory of which isolates contain the genes of interest. Of course, I’m not going to do that myself, but if you’d like to get started in your own lab I’d be more than happy to help!

What's Big about Small Proteins?

Something interesting has been happening in the world of microbiome research, and it’s all about small proteins.

What’s New?

There was a paper in my weekly roundup of microbiome publications which caught my eye:

Petruschke, H., Schori, C., Canzler, S. et al. Discovery of novel community-relevant small proteins in a simplified human intestinal microbiome. Microbiome 9, 55 (2021).

Reading through the abstract, the authors have “a particular focus on the discovery of novel small proteins with less than 100 amino acids.” While this may seem to be a relatively innocuous statement, I was very interested to see what they found because of some recent innovations in the computational approaches used to study the microbiome.

What’s the Context?

When people study the microbiome, they often only have access to the genome sequences of the bacteria which are present. This is very much the case for the type of metagenomic analysis which I focus on, as with any approach which takes advantage of the massive amounts of data which can be generated with genome sequencing instruments.

When analyzing bacterial genomes, we are able to predict what genes are contained in each genome using annotation tools designed for this purpose. The most commonly used tool for this task is Prokka, made by Torsten Seemann. Recently, researchers have started to realize that there are some bacterial proteins which were being missed by these types of approaches, since the experimental data used to build the predictive models did not include a whole collection of small proteins.

Then, in 2019 Dr. Ami Bhatt’s group at Stanford published a high-profile paper making the case that microbiome analyses were systematically omitting small bacterial proteins:

Sberro H, Fremin BJ, Zlitni S, Edfors F, Greenfield N, Snyder MP, Pavlopoulos GA, Kyrpides NC, Bhatt AS. Large-Scale Analyses of Human Microbiomes Reveal Thousands of Small, Novel Genes. Cell. 2019 Aug 22;178(5):1245-1259.e14. doi: 10.1016/j.cell.2019.07.016. Epub 2019 Aug 8. PMID: 31402174; PMCID: PMC6764417.

Around the same time, other groups were publishing studies which used other experimental approaches which supported the idea that bacteria encoded these small genes, which were also being transcribed and translated as bona fide proteins (a few quick examples).

What’s the Point?

The reason I think this story is worth mentioning is because it shines light on part the foundation of microbiome research. When we conduct a microbiome experiment, we can only make a limited number of measurements. We then do the best job we can to infer the biological features which are relevant to our experimental question. Part of the revolution of microbiome research from the last ten years has been the explosion of metagenomic data which is now available. This research is particularly interesting because it shows us how our analysis of that data may have been missing an entire class of genetic elements — genes which encode proteins less than 100 amino acids in length.

At the end of the day, the message is a positive one: with improved experimental techniques we can now generate more useful and accurate data from existing datasets. I am looking forward to seeing what we are able to find as the field continues to explore this new area of the microbiome!

Quality and Insights – The Human Gut Virome in 2019

There were a couple of good virome papers I read this week, and I thought it was worth commenting on the juxtaposition.

Virome — The collection of viruses which are found in a complex microbial community, such as the human microbiome. NB: Most viruses found in any environment are bacteriophages — the viruses which infect bacteria, and do not infect humans.

Measuring Quality, Measuring Viruses

https://www.nature.com/articles/s41587-019-0334-5

I was excited to see two of my favorite labs collaborating on a virome data quality project: the Bushman lab at the University of Pennsylvania (where I trained) and the Segata lab at the University of Trento (who originally made MetPhlAn, the first breakthrough software tool for microbial metagenomics). The goal of this work was to measure the quality of virome research projects.

Virome research projects over the last decade have relied on a technological approach in which viral particles are physically isolated from a complex sample and then loaded onto a genome sequencer. There are a variety of experimental approaches which you can use to isolate viruses, including size filtration and density gradient centrifugation, which rely on the fact that viruses are physically quite different from bacterial cells.

The question asked by the researchers in this study was, “How well are these physical isolation methods actually working?” It’s such a good question that I’m surprised (in retrospect) that nobody had asked it before. As someone who has worked a bit in this area, I’m also surprised that I never thought to ask this question before.

Their approach was nice and straightforward — they looked in these datasets for sequences that should not be found very often, those belonging to the bacterial ribosome, whose absence is almost required in order to be considered a virus.

They found that the quality of these virome datasets varied extremely widely. You can read the paper for more details, and I am hesitant to post the figures on a public blog, but I really did not expect to see that there were published virome datasets with proportions of ribosomal sequences ranging from 0.001% all the way up to 1%.

Take Home: When you use a laboratory method to study your organism of interest, you need to use some straightforward approach for proving to yourself and others that it is actually working as you expect. For something as challenging and complex as the human virome, this new QC tool might help the field maintain a high standard of quality and avoid misleading or erroneous results.

Viral Dark Matter in IBD

https://www.sciencedirect.com/science/article/pii/S1931312819305335

One of the best talks I saw at ASM Microbe 2019 was from Colin Hill (APC Microbiome Ireland) and so I was happy to see a new paper from that group analyzing the gut virome in the context of Inflammatory Bowel Disease. I was even more gratified to read the abstract and see some really plausible and defensible claims being made in an area which is particularly vulnerable to over-hype.

1-s2.0-S1931312819305335-fx1_lrg.jpg

No Change in Richness in IBD: Microbiome researchers talk a lot about “richness,” which refers to the total number of distinct organisms in a community. This metric can be particularly hard to nail down with viruses because they are incredibly diverse and we have a hard time counting how many “types” there are (or even what being a “type” means). In this paper they used the very careful approach of re-assembling all viral genomes from scratch, rather than comparing against an existing database, and found that there was no difference in the richness of the virome in IBD vs. non-IBD samples. When others have analyzed the same data with methods that relied on reference databases, they found a significant difference in richness, which suggests that the database was confounding the results for those prior studies.

Changes in Viruses Reflect Bacteria: The authors state that “the changes in virome composition reflected alterations in bacterial composition,” which resonated with me so strongly that I think it merits mentioning again here. Viruses tend to be extremely specific and only infect a subset of strains within a species of bacteria. They are also so diverse that it is hard to even figure out which virus is infecting which bacteria. Therefore, with our current level of understanding and technology, viruses in the human gut are really best approached as a marker of what bacterial strains are present. It’s hard to get anything more concrete than that from sequencing-based approaches, except with some specific examples of well-understood viruses. With that limitation of our knowledge in mind, it is entirely expected that changes in bacteria would be reflected in changes in their viruses. Moreover, in this type of observational study we don’t have any way to figure out which direction the arrow of directionality is pointing. I think the authors did a great job of keeping their claims to the limits of our knowledge without over-hyping the results.

There is a lot more to this paper, so I encourage you to read it in more depth and I won’t claim to make a full summary here.

In Summary: This is a fascinating field, with some really great groups doing careful and important work. We know a lot about how little we know, which means that there are even more exciting discoveries on the horizon.

3D structures of gut bacteria and the human immune system

When I talk to people about my work I sometimes get the question, “Do you really think that the microbiome has a direct effect on human health?” It’s a completely understandable question – the study-of-the-week which makes it into the news cycle tends to just confirm what we already know about the importance of diet and exercise. Then I come across these beautiful papers that show just how intimately connected we are with our gut bacteria. Here’s a good example, and it even comes with a video.

Ladinsky, M.S., et al. Endocytosis of commensal antigens by intestinal epithelial cells regulates mucosal T cell homeostasis. Science. 363(6431). DOI: 10.1126/science.aat4042.

There are some beautiful illustrations and graphics in this paper which I won’t reproduce here, but which I hope you can access from whichever side of the paywall you are on.

Background: Researchers are continuing to find evidence that the type of bacteria in your gut (if you are a mouse or a human) influences the type of your immune response. If you don’t study the immune system, just remember that the immune system responds in different ways to different kinds of pathogens – viruses are different from bacteria, which are different from parasites, etc. Mounting the correct type of response is essential, and it seems that which bacteria you have in your gut has some influence over the nature of those responses.

The Gist: This study focused on the how of the question, the specific molecular mechanism which would explain this observed relationship between bacteria and the immune system. They used one particular type of bacteria (segmented filamentous bacteria, or “SFB”) and showed that this bacteria gets so close to human cells that bacterial proteins are actually taken up and can be found inside the human cells. In addition, this movement of bacterial proteins inside human cells causes a shift in the type of response mounted by the immune system.

What Caught My Eye: This paper has a video showing a protrusion of a bacterial cell pushing deep into a human cell, complete with a 3D reconstruction of the physical structure using electron tomography. If you can follow the link above and make it to the video, I highly recommend taking a look.

The biggest story for me in the microbiome these days is that there are a number of great researchers who are starting to figure out some of the specific molecular mechanisms by which the microbiome may influence human health. This makes me more and more optimistic and excited that we will see a day where microbiome-based therapeutics make it into the clinic, which could have a profound impact on a broad range of diseases, from inflammatory bowel disease to colorectal cancer and auto-inflammatory disease. It is exciting to be a part of this effort and try to help as we bring that day closer.

Molecules Mediating Microbial Manipulation of Mouse (and Human) Maladies

Sometime in the last ten years I gave up on the idea of truly keeping up with the microbiome field. In graduate school it was more reasonable because I had the luxury of focusing on viruses in the microbiome, but since then my interests have broadened and the size of the field has continued to expand. These days I try to focus on the subset of papers which are telling the story of either gene-level metagenomics, or the specific metabolites which mediate the biological effect of the microbiome on human health. The other day I happened across a paper which did both, and so I thought it might be worth describing it quickly here.

Brown, EM, et al. Bacteroides-Derived Sphingolipids Are Critical for Maintaining Intestinal Homeostasis and Symbiosis. Cell Host & Microbe 2019 25(5) link

As a human, my interest is drawn by stories that confirm my general beliefs about the world, and do so with new specific evidence. Of course this is the fallacy of ascertainment bias, but it’s also an accurate description of why this paper caught my eye.

The larger narrative that I see this paper falling into is the one which says that microbes influence human health largely because they produce a set of specific molecules which interact with human cells. By extension, if you happen to have a set of microbes which cannot produce a certain molecule, then your health will be changed in some way. This narrative is attractive because it implies that if we understand which microbes are making which metabolites (molecules), and how those metabolites act on us, then we can design a therapeutic to improve human health.

Motivating This Study

Jumping into this paper, the authors describe a recently emerging literature (which I was unaware of) on how bacterially-produced sphingolipids have been predicted to influence intestinal inflammation like IBD. Very generally, sphingolipids are a diverse class of molecules that can be found in bacterial cell membranes, but which also can be produced by other organisms, and which also can have a signaling effect on human cells. The gist of the prior evidence going into this paper is that

  • people with IBD have lower levels of different sphingolipids in their stool, and

  • genomic analysis of the microbiome of people with IBD predicts that their bacteria are making less sphingolipids

Of course, those observations don’t go very far on their own, mostly because there are a ton of things that are different in the microbiome of people with IBD, and so it’s hard to point to any one bacteria or molecule from the bunch and say that it is having a causal role, and isn’t just a knock-on effect from some other cause.

The Big Deal Here

The hypothesis in this study is that one particular type of bacteria, Bacteroides are producing sphingolipids which reduce inflammation in the host. The experimental system they used were mice that were born completely germ-free, and which were subsequently colonized with strains of Bacteroides that either did or did not have the genes required to make some particular types of sphingolipids. The really cool thing here was that they were able to knock out the gene for sphingolipid production in one specific species of Bacteroides, and so they could see what the effect was of that particular set of genes, while keeping everything else constant. They found a pretty striking result, which is that inflammation was much lower in the mice which were colonized with the strain which was able to make the sphingolipid.

1-s2.0-S1931312819302057-fx1_lrg.jpg


To me, narrowing down the biological effect in an experiment to the difference of a single gene is hugely motivating, and really makes me think that this could plausibly have a role in the overall phenomenon of microbiome-associated inflammation.

The authors rightly point out that sphingolipids might not actually be the molecular messenger having an impact on host physiology — there are a lot of other things different in the sphingolipid-deficient bacteria used here, including carbohydrate metabolism and membrane composition, but it’s certainly a good place to keep looking.

Of course the authors did a bunch of other work in this paper to demonstrate that the experimental system was doing what they said, and they also went on to re-analyze the metabolites from human stool and identify specific sphingolipids that may be produced by these Bacteroides species, but I hope that my short summary gives you an idea of what they are getting at.

All About Those Genes

I think it can be difficult for non-microbiologists to appreciate just how much genetic diversity there is among bacteria. Strains which seem quite similar can have vastly different sets of genes (encoding, for example, a giant harpoon used to kill neighboring cells), and strains which seem quite different may in fact be sharing genes through exotic forms of horizontal gene transfer. With all of this complexity, I find it very comforting when scientists are able to conduct experiments which identify specific molecules and specific genes within the microbiome which have an impact on human health. I think we are moving closer to a world where we are able to use our knowledge of the microbiome to improve human health, and I think studies like this are bringing us closer.

Preprint: Identifying genes in the human microbiome that are reproducibly associated with human disease

I’m very excited about a project that I’ve been working on for a while with Prof. Amy Willis (UW - Biostatistics), and now that a preprint is available I wanted to share some of that excitement with you. Some of the figures are below, and you can look at the preprint for the rest.

Caveat: There are a ton of explanations and qualifications that I have overlooked for the statements below — I apologize in advance if I have lost some nuance and accuracy in the interest of broader understanding.

Big Idea

When researchers look for associations of the microbiome with human disease, they tend to focus on the taxonomic or metabolic summaries of those communities. The detailed analysis of all of the genes encoded by the microbes in each community hasn’t really been possible before, purely because there are far too many genes (millions) to meaningfully analyze on an individual basis. After a good amount of work I think that I have found a good way to efficiently cluster millions of microbial genes based on their co-abundance, and I believe that this computational innovation will enable a whole new approach for developing microbiome-based therapeutics.

Core Innovation

I was very impressed with the basic idea of clustering co-abundant genes (to form CAGs) when I saw it proposed initially by one of the premier microbiome research groups. However, the computational impossibility of performing all-by-all comparisons for millions of microbial genes (with trillions of potential comparisons) ultimately led to an alternate approach which uses co-abundance to identify “metagenomic species” (MSPs), a larger unit that uses an approximate distance metric to identify groups of CAGs that are likely from the same species.

That said, I was very interested in finding CAGs based on strict co-abundance clustering. After trying lots of different approaches, I eventually figured out that I could apply the Approximate Nearest Neighbor family of heuristics to effectively partition the clustering space and generate highly accurate CAGs from datasets with millions of genes across thousands of biological samples. So many details to skip here, but the take-home is that we used a new computational approach to perform dimensionality reduction (building CAGs), which made it reasonable to even attempt gene-level metagenomics to find associations of the microbiome with human disease.

Just to make sure that I’m not underselling anything here, being able to use this new software to perform exhaustive average linkage clustering based on the cosine distance between millions of microbial genes from hundreds of metagenomes is a really big deal, in my opinion. I mostly say this because I spent a long time failing at this, and so the eventual success is extremely gratifying.

Associating the Microbiome with Disease

We applied this new computational approach to existing, published microbiome datasets in order to find gene-level associations of the microbiome with disease. The general approach was to look for individual CAGs (groups of co-abundant microbial genes) that were significantly associated with disease (higher or lower in abundance in the stool of people with a disease, compared to those people without the disease). We did this for both colorectal cancer (CRC) and inflammatory bowel disease (IBD), mostly because those are the two diseases for which multiple independent cohorts existed with WGS microbiome data.

Discovery / Validation Approach

The core of our statistical analysis of this approach was to look for associations with disease independently across both a discovery and a validation cohort. In other words, we used the microbiome data from one group of 100-200 people to see if any CAGs were associated with disease, and then we used a completely different group of 100-200 people in order to validate that association.

Surprising Result

Quite notably, those CAGs which were associated with disease in the discovery cohort were also similarly associated with disease in the the validation cohort. These were different groups of people, different laboratories, different sample processing protocols, and different sequencing facilities. With all of those differences, I am very hopeful that the consistencies represent an underlying biological reality that is true across most people with these diseases.

Figure 2A: Association of microbial CAGs with host CRC across two independent cohorts.

Figure 2A: Association of microbial CAGs with host CRC across two independent cohorts.

Developing Microbiome Therapeutics: Linking Genes to Isolates

While it is important to ensure that results are reproducible across cohorts, it is much more important that the results are meaningful and provide testable hypotheses about treating human disease. The aspect of these results I am most excited about is that each of the individual genes that were associated above with CRC or IBD can be directly aligned against the genomes of individual microbial isolates. This allows us to identify those strains which contain the highest number of genes which are associated positively or negatively with disease. It should be noted at this point that observational data does not provide any information on causality — the fact that a strain is more abundant in people with CRC could be because it has a growth advantage in CRC, it could be that it causes CRC, or it could be something else entirely. However, this gives us some testable hypotheses and a place to start for future research and development.

Figure 3C: Presence of CRC-associated genes across a subset of microbial isolates in RefSeq. Color bar shows coefficient of correlation with CRC.

Figure 3C: Presence of CRC-associated genes across a subset of microbial isolates in RefSeq. Color bar shows coefficient of correlation with CRC.

Put simply, I am hopeful that others in the microbiome field will find this to be a useful approach to developing future microbiome therapeutics. Namely,

  1. Start with a survey of people with and without a disease,

  2. Collect WGS data from microbiome samples,

  3. Find microbial CAGs that are associated with disease, and then

  4. Identify isolates in the freezer containing those genes.

That process provides a prioritized list of isolates for preclinical testing, which will hopefully make it a lot more efficient to develop an effective microbiome therapeutic.

Thank You

Your time and attention are appreciated, as always, dear reader. Please do not hesitate to be in touch if you have any questions or would like to discuss anything in more depth.

Massive unexplored genetic diversity of the human microbiome

When you analyze extremely large datasets, you tend to be guided by your intuition or predictions on how those datasets are composed, or how they will behave. Having studied the microbiome for a while, I would say that my primary rule of thumb for what to expect from any new sample is tons of novel diversity. This week saw the publication of another great paper showing just how true this is.

Extensive Unexplored Human Microbiome Diversity Revealed by Over 150,000 Genomes from Metagenomes Spanning Age, Geography, and Lifestyle Resource

graphical_abstract.jpg

The Approach

If you are new to the microbiome, you may be interested to know that there are basically two approaches to figuring out what microbes (bacteria, viruses, etc.) are in a given sample (e.g. stool). You can either (1) compare all of the DNA in that sample to a reference database of microbial genomes, or (2) try to reassemble the genomes in each sample directly from the DNA.

The thesis of this paper is one that I strongly support: reference databases contain very little of the total genomic content of microbes out there in the world. By extension, they predict that (1) would perform poorly, while (2) will generate a much better representation of what microbes are present.

Testing this idea, the authors analyzed an immense amount of microbiome data (almost 10,000 biological samples!), performing the relatively computationally intensive task of reconstructing genomes (so-called _de novo_ assembly).

The Results

The authors found a lot of things, but the big message is that they were able to reconstruct a *ton* of new genomes from these samples — organisms that had never been sequenced before, and many that don’t really resemble any phyla that we know of. In other words, they found a lot more novel genomic content than even I expected, and I was sure that they would find a lot.

gr1.jpg

There’s a lot more content here for microbial genome afficianados, so feel free to dig in on your own (yum yum).

Take Home

When you think about what microbes are present in the microbiome, remember that there are many new microbes that we’ve never seen before. Some of those are new strains of clearly recognizable species (e.g. E. coli with a dozen new genes), but some will be novel organisms that have never been cultured or sequenced by any lab.

If you’re a scientist, keep that in mind when you are working in this area. If you’re a human, take hope and be encouraged by the fact that there is still a massive undiscovered universe within us, full of potential and amazing new things waiting to be discovered.

Niche Theory and the Human Gut Microbiome

Without really having the time to write a full blog post, I want to mention two recent papers that have strongly influenced my understanding of the microbiome.

Niche Theory

The ecological concept of the “niche” is something that is discussed quite often in the field of the microbiome, namely that each bacterial species occupies a niche, and any incoming organism trying to use that same niche will be blocked from establishing itself. The mechanisms and physical factors that cause this “niche exclusion” is probably much more clearly described in the ecological study of plants and animals — in the case of the microbiome I have often wondered just what utility or value this concept really had.

That all changed a few weeks ago with a pair of papers from the Elinav group.

The Papers

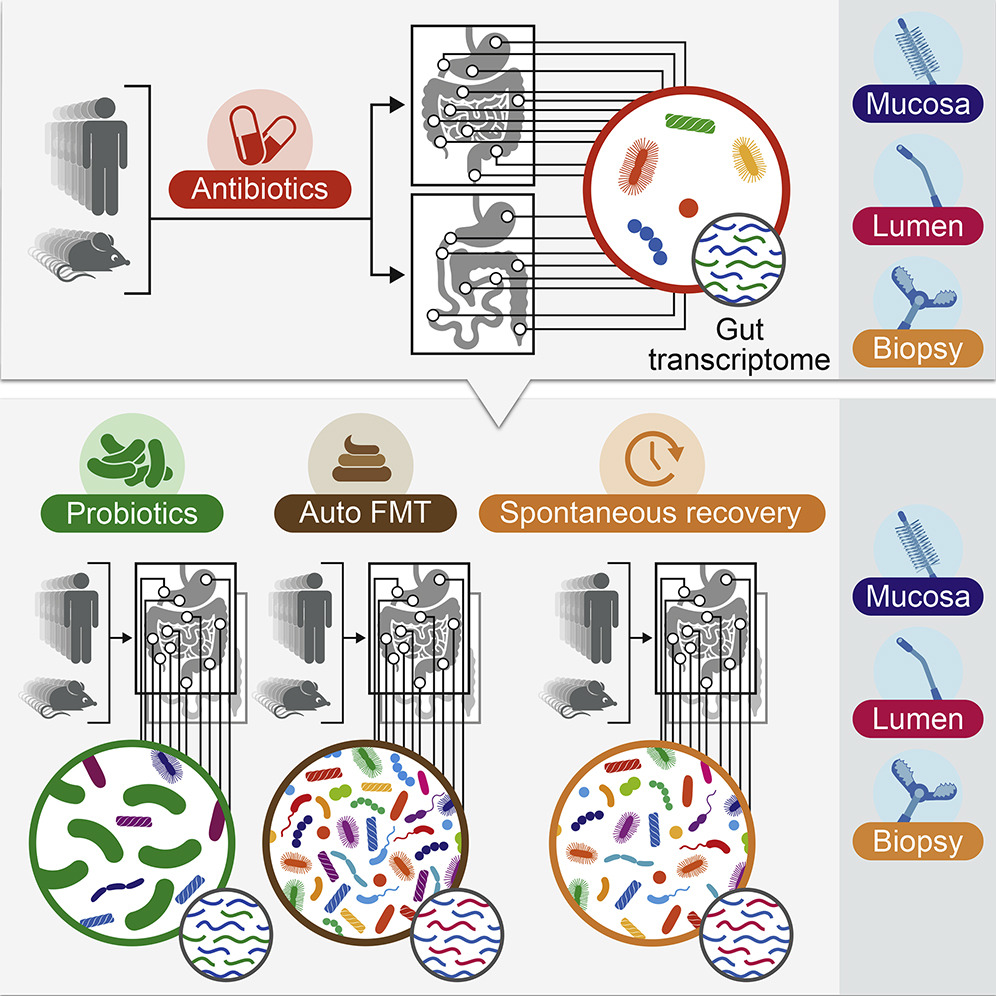
Personalized Gut Mucosal Colonization Resistance to Empiric Probiotics Is Associated with Unique Host and Microbiome Features

1-s2.0-S0092867418311024-fx1_lrg.jpg
1-s2.0-S0092867418311085-fx1_lrg.jpg

Quick, Quick Summary

At the risk of oversimplifying, I’ll try to summarize the two biggest points I took home from these papers.

  1. Lowering the abundance and diversity of bacteria in the gut can increase the probability that a new strain of bacteria (from a probiotic) is able to grow and establish itself

  2. The ability of a new bacteria (from a probiotic) to grow and persist in the gut varies widely on a person-by-person basis

Basically, the authors showed quite convincingly that the “niche exclusion” effect does indeed happen in the microbiome, and that the degree of niche exclusion is highly dependent on what microbes are present, as well as a host of other unknown factors.

So many more questions

Like any good study, this raises more questions than it answers. What genetic factors determine whether a new strain of bacteria can grow in the gut? Is it even possible to design a probiotic that can grow in the gut of any human? Are the rules for “niche exclusion” consistent across bacterial species or varied?

As an aside, these studies demonstrate the consistent observation that probiotics generally don’t stick around after you take them. If you have to take a probiotic every day in order to sustain its effect, it’s not a real probiotic.

I invite you to read over these papers and take what you can from them. If I manage to put together a more lengthy or interesting summary, I’ll make sure to post it at some point.

Microbiome Research: Hope over Hype

The story of microbiome research is one of hope and hype, both elevated to an extreme and fraught with controversy. You need look no further than popular blogs and high profile review articles to see this conflict play out. 

As a passionate microbiome researcher, I like to highlight the hope that I see -- the hope that humans will be able to understand and harness the microbiome to improve human health. 

The story of hope I have for you today is a story of the heart. The human heart. Well, heart disease. Reducing heart disease, really.

Setup

When I was in graduate school I saw the most fascinating lecture. It was from Stanley Hazen, a researcher at the Cleveland Clinic, and he was describing an experiment in which it appeared that bacteria in the gut were responsible for converting a normal part of our diet into a molecule that promoted atherosclerosis (heart disease). With a combination of (1) molecular analysis of the blood of humans with heart disease and (2) experiments in mice varying the diet and microbes present in the gut, they showed pretty convincingly that bacteria were converting phosphatidylcholine from food into TMAO, which then promoted heart disease (Wang, et al. 2011 Nature). 

Payoff

Fast forward 7 years, and the microbiome research field has advanced far enough to identify the exact bacterial genes involved in this process. Not only that, they are able to inhibit those specific bacterial enzymes and show in a mouse model that levels of harmful TMAO are pushed down as a result (Roberts, et al. 2018 Nature).

Fig. 5: A microbial choline TMA lyase inhibitor reverses diet-induced changes in cecal microbial community composition associated with plasma TMAO levels, platelet responsiveness, and in vivo thrombosis potential. Schematic of the relationship …

Fig. 5: A microbial choline TMA lyase inhibitor reverses diet-induced changes in cecal microbial community composition associated with plasma TMAO levels, platelet responsiveness, and in vivo thrombosis potential. Schematic of the relationship between human gut commensal choline TMA lyase activity, TMA and TMAO generation, and enhanced platelet responsiveness and thrombosis risk in the host

Bioinformatics Aside

One aspect of this story that I'll point out for the bioinformatics folks in the audience is that the biological mechanism involved in choline -> TMAO is not a phylogenetically conserved one. It is mediated by a set of genes that are distributed sporadically across the bacterial tree of life. For that reason and others, I am a strong supporter of microbiome analysis tools that enable gene-level comparison between large sets of samples in order to identify mechanisms like these in the future. 

Summary

My hope, my dream, is that the entire human microbiome field is able to eventually follow this path. We observe that the microbiome influences some aspect of human health, we identify the biological mechanism responsible for this effect, and then we demonstrate our knowledge and mastery of this biology to such an extent that we can intentionally manipulate this system and eventually improve human health. 

We have a long way to go, but I believe that this is the path that we can follow, the example we can aspire to. I hope that this story gives you hope, and helps cut through the hype.